



An AI driven EHR is an electronic health record that uses AI to draft notes, summarize charts, suggest codes, prioritize inbox messages and flag patients at risk, with a clinician reviewing every output before it enters the record. Making it safe depends on BAAs with AI vendors, transparent decision support, testing for accuracy and bias, and monitoring.
This AI driven EHR guide explains how EHR vendors are adding AI, the rules that apply, how to build an EHR AI scribe, whether to build AI into a custom EHR or add it to an existing one, best practices and the mistakes to avoid.
What is an AI driven EHR?
Adding AI to your EHR workflows?
We integrate AI features with Epic, Oracle Health and other EHRs through FHIR, with review and audit built in.
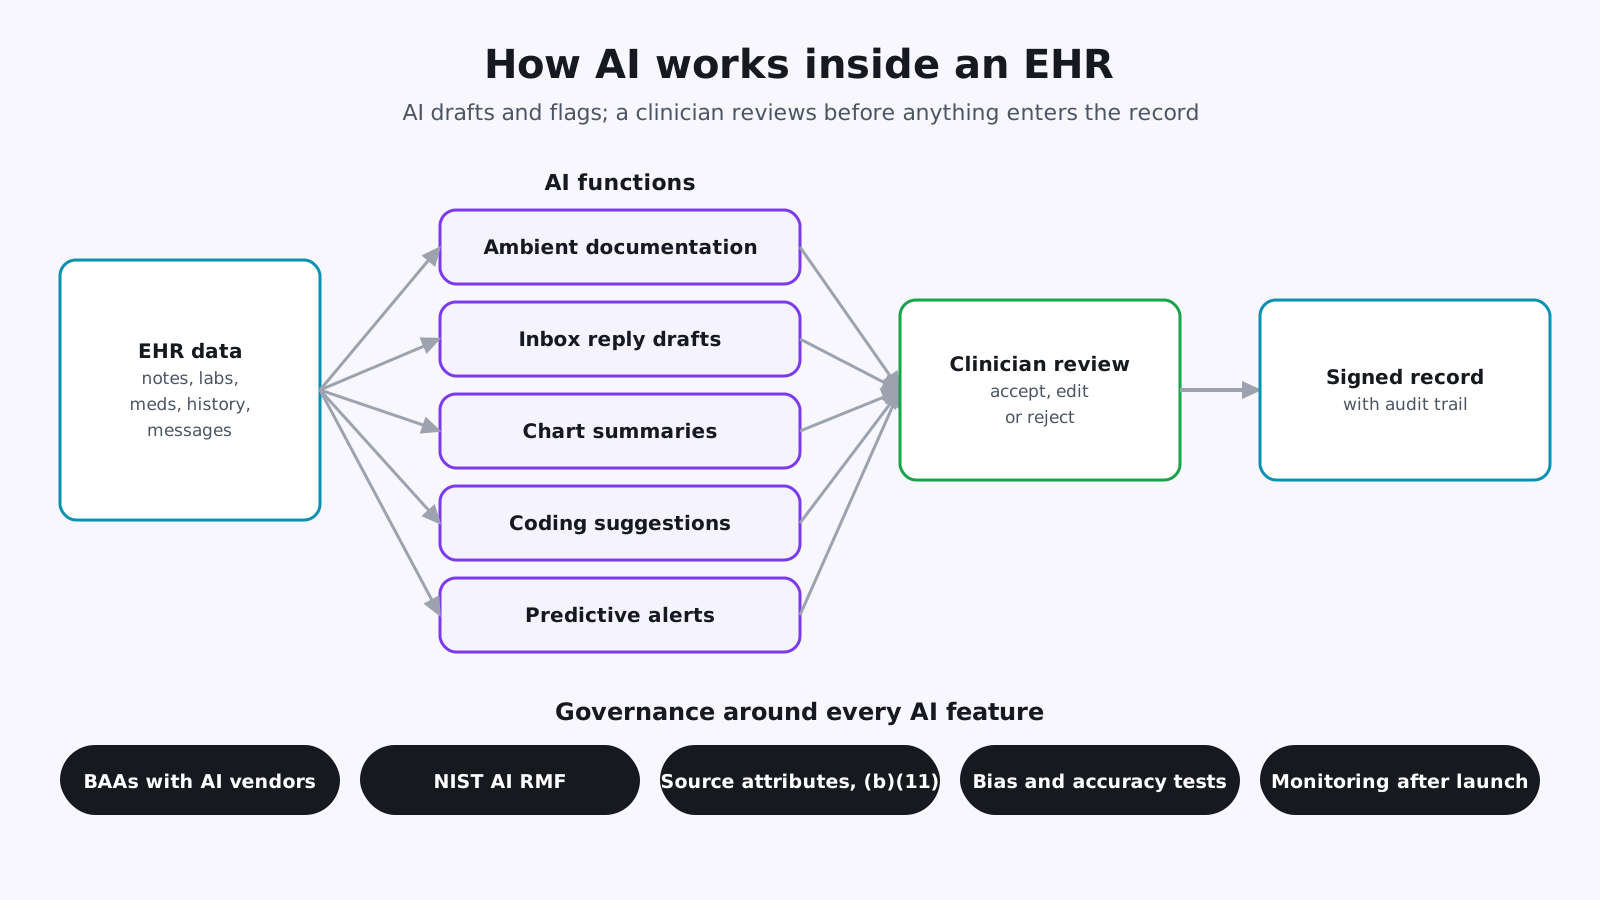
What is an AI driven EHR, compared with an EHR that simply has an AI add-on? The difference is how deeply AI sits in daily work. In an AI driven EHR, AI drafts the first version of routine documents and highlights what needs attention, while the clinician stays the decision maker and signs what goes into the chart.
How EHR vendors are adding AI
Oracle announced a new AI-powered EHR in October 2024 and launched it in August 2025. Oracle says that version received ONC Health IT certification on October 3, 2025 for US ambulatory clinics, and that its Clinical AI Agent drafts notes from the visit conversation, with coding suggestions, dictation and chart review added in August 2026. Epic describes generative AI assistants built into its software: Art for clinicians, which drafts message replies and visit notes, Emmie for patients in MyChart, and Penny for revenue cycle work. Availability of these features varies by organization.
Common uses of AI in EHR workflows
- Ambient documentation: Drafting a visit note from the recorded conversation.
- Inbox support: Drafting replies to patient messages and sorting messages by urgency.
- Chart summaries: Summarizing a long history before a visit or handoff.
- Coding suggestions: Proposing diagnosis and procedure codes from the documentation.
- Predictive alerts: Flagging patients at higher risk, such as for readmission or deterioration.
- Search: Answering questions about a patient's record in plain language.
Why does AI in the EHR matter now?
AI in EHR systems now sits under several rules and frameworks:
- Decision support transparency: Under the ASTP/ONC HTI-1 rule, ONC Health IT Certification criterion 170.315(b)(11) requires certified health IT to support source attributes for predictive decision support interventions, plain-language details about a model's purpose, data, validation and fairness. The HTI-5 proposed rule of December 2025 would remove these requirements, but it was not final as of October 2026.
- Nondiscrimination: The Section 1557 rule (45 CFR 92.210) requires covered entities to make reasonable efforts to identify decision support tools that use race, color, national origin, sex, age or disability as inputs and to reduce the risk of discrimination. The compliance date was May 1, 2025.
- FDA scope: The FDA issued final Clinical Decision Support Software guidance in January 2026. It explains which decision support functions for health care professionals are not medical devices, while software aimed at patients or caregivers still falls under device policy.
- Vendor agreements: An AI vendor that creates, receives, maintains or transmits PHI for a covered entity is a business associate and must sign a Business Associate Agreement (45 CFR 164.502(e)).
- AI risk management: The NIST AI RMF gives organizations a voluntary structure to govern, map, measure and manage AI risks.
How do you build an EHR AI scribe?
To build an EHR AI scribe, treat it as a clinical documentation workflow, not just a speech to text feature:
- 1. Consent and recording: Tell patients the visit is recorded and get consent. State recording laws differ, so confirm the rules where you operate.
- 2. Capture and transcription: Record clear audio on approved devices and transcribe it with a vendor covered by a BAA.
- 3. Note generation: Turn the transcript into a draft in the organization's note templates, separating what was said from what the model inferred.
- 4. Clinician review: Show the draft beside the source so the clinician can check, edit and sign it.
- 5. Filing to the EHR: File the signed note through the EHR's API, for example as a FHIR DocumentReference, or through the vendor's documentation interface.
- 6. Audit and retention: Log who generated, edited and signed each note, and decide how long audio and transcripts are kept.
- 7. Quality measurement: Track edit rates, errors found in review and clinician feedback, and retest after model changes.
We found no CMS or HHS rule written specifically for ambient AI scribes. Existing rules on documentation, signatures, medical necessity and HIPAA still apply, and the clinician who signs the note remains responsible for it.
Should you build AI into a custom EHR or add it to an existing one?
- Use the vendor's AI: Fastest when your EHR already offers the feature you need, but you depend on its roadmap and licensing.
- Add AI apps around the EHR: Build AI tools that read data through FHIR APIs, an HL7 International standard, and SMART on FHIR, and write results back through supported interfaces. This fits most specialty needs.
- Build an AI custom EHR: Design AI into a custom EHR from the start. Most control, but you also own certification, safety testing and maintenance.
Most organizations combine the first two: vendor AI for common tasks, and custom AI apps for specialty workflows the vendor does not cover.
Measuring whether AI helps
Decide before launch how you will know the feature works. Useful measures include time spent on documentation or the inbox, how often clinicians edit or reject AI output, errors found in review, and clinician and patient feedback. Compare with a baseline taken before the pilot, and review the results with clinical leaders before expanding.
How do teams approach an AI driven EHR project step by step?
- 1. Pick one workflow: Choose a task with clear time cost and clear review, such as inbox replies or visit notes.
- 2. Define success: Agree on measures such as time saved, edit rate and safety events before you start.
- 3. Check the rules: Confirm FDA status, decision support transparency needs and nondiscrimination duties for the feature.
- 4. Choose vendors: Select model and transcription vendors that sign BAAs and meet your data retention needs.
- 5. Integrate with the EHR: Read data through FHIR APIs and file results through supported interfaces, with the health system's approval.
- 6. Build review into the screen: Make it easy to compare the AI output with the source and to reject it.
- 7. Test before launch: Test accuracy and bias across patient groups with realistic data.
- 8. Pilot and monitor: Start with a small group of clinicians, monitor quality and usage, and expand when results hold.
What are AI driven EHR best practices?
- Human in the loop: Nothing AI generated enters the record without a clinician's review.
- Show the source: Link summaries and suggestions to the data they came from.
- Send the minimum: Give models only the data each task needs.
- Log everything: Record inputs, outputs, edits and sign-offs for audits.
- Monitor over time: Model quality can change with new data, workflows or vendor updates.
- Accessible design: Build AI features into screens that meet WCAG 2.2 so every clinician and patient can use them.
What are the common mistakes with AI in the EHR?
- Starting with the model: Choosing an AI tool before defining the workflow and the measure of success.
- No BAA: Sending PHI to an AI service without a signed Business Associate Agreement.
- Hidden reasoning: Showing suggestions without the data or source behind them.
- Testing on one group: Validating a model on one patient population and using it on others.
- Too many alerts: Adding predictive alerts that clinicians learn to ignore.
- No owner after launch: Nobody watching quality once the pilot ends.
- Ignoring the record's legal role: Treating AI drafts as final, when the signed note is the legal record the clinician is responsible for.
What does an AI driven EHR mean for your build plan?
- Use cases: The number of AI features and the workflows they touch.
- EHR integration: The EHRs involved, the APIs they offer and the approvals each site requires.
- Vendors: Model, transcription and hosting vendors, with BAAs and retention terms.
- Governance: Transparency details, bias testing, review workflows and monitoring.
- Regulatory review: FDA status, Section 1557 duties and certification needs.
- Change management: Training clinicians and measuring adoption.
How Agnotic can help
Agnotic Technologies is a software development services company. We build AI features that work with EHRs: integrations with Epic, Oracle Health and other systems through FHIR, AI scribes and inbox tools with clinician review, audit logging and HIPAA safeguards, and the testing and monitoring around them. You own the code; we build it around your clinical workflows.
Build AI into your EHR workflows with Agnotic
Explore our EHR integration services or browse more articles in our EHR integration hub.
Related reading on Agnotic
Go deeper on the AI, integration and compliance topics covered in this guide.
Sources
- Oracle: ONC certification of Oracle's AI-powered EHR
- Oracle: Clinical AI Agent adds coding, dictation and chart review
- Epic: AI for clinicians
- ASTP/ONC: Decision support interventions, 170.315(b)(11)
- ASTP/ONC HTI-5 Proposed Rule
- 45 CFR 92.210: Nondiscrimination in the use of patient care decision support tools
- FDA Clinical Decision Support Software Guidance
- NIST AI Risk Management Framework


