

RPM service companies
Automated billing across a large monitored population.


RPM programs lose revenue when device days, management minutes and consent are not recorded the way each CPT code requires. We build RPM billing software that tracks all three in the product and hands your billing team clean, audit-ready 837P claims.
Trusted by global innovators









RPM billing software records the evidence each remote patient monitoring CPT code needs: consent and setup, the days a device sent readings in each 30-day period, and the minutes of management time. Agnotic Technologies builds this tracking into your RPM product, so claims follow the CY 2026 Medicare code rules and hold up in an audit.
For 2026, Medicare pays RPM device supply through CPT 99454 (16 to 30 days of readings) and 99445 (2 to 15 days), and management time through 99470 (first 10 minutes), 99457 (first 20 minutes) and 99458 (each additional 20 minutes).
The codes
Each RPM code maps to one piece of program work. 99453 is the one-time setup and patient education. 99454 and 99445 are the monthly device supply codes, split by days of readings, and 99470, 99457 and 99458 cover management time in a calendar month.
Getting paid means proving each element: setup happened once, the device-day count fits the code billed, and the minutes were spent and documented. We build the tracking and evidence for every code, so your billing team checks claims instead of rebuilding them.
See how device readings and clinician time flow through day-count and timer logic into clean RPM CPT claims.

Every rule that decides whether an RPM claim gets paid, encoded in the product.
One-time setup and patient education billed once per episode, with logic that prevents duplicate 99453 charges across a patient's monitoring lifetime.
Automatic counting of days with readings in each 30-day period, so the right device supply code applies (99454 for 16 to 30 days, 99445 for 2 to 15) and at-risk patients are flagged before the window closes.
A per-patient, per-calendar-month timer that records management minutes and applies 99470 for the first 10 minutes or 99457 for the first 20, then 99458 for each additional 20, with a documented interaction log.
Pre-claim checks for consent, established-patient status, and code-combination rules that catch the errors payers deny for, before the claim is submitted.
Clean X12 837P professional claims with modifiers and ICD-10 linkage, plus an immutable audit trail so every billed minute and reading is defensible under review.
Where it runs
Automated billing across a large monitored population.
Enterprise billing tied to existing revenue cycle.
Recurring monthly RPM billing for chronic conditions.
In-practice RPM billing without a separate biller.
Bolt-on billing accuracy for a platform missing it.
RPM billing alongside quality and outcome tracking.
Days of readings and documented minutes decide which RPM code applies in a month. We count both automatically.

Health Insurance Portability and Accountability Act
Protect PHI with privacy-first architecture, encrypted storage and transmission, strict access controls, and traceable audit logs.

General Data Protection Regulation
Implement lawful consent flows, data minimization, retention controls, and secure processing for sensitive health data.

Fast Healthcare Interoperability Resources
Enable standardized health data exchange across apps, care teams, and systems through standards-based FHIR APIs.

Health Level Seven International
Support enterprise-grade interoperability with HL7-based integrations for records, events, and clinical messaging workflows.

Health Information Trust Alliance
Align security programs to healthcare-specific control and risk management practices trusted by providers and ecosystem partners.

Health Information Technology for Economic and Clinical Health Act
Design with breach notification readiness, digital record safeguards, and operational controls that support regulated care programs.

FDA Software as a Medical Device
Plan software quality, traceability, and documentation pathways for products that may require SaMD review and submission.

Medical Device Regulation (European Union)
Prepare EU market-ready processes for risk classification, evidence tracking, and lifecycle governance under MDR expectations.

Substance Abuse and Mental Health Services Administration
Apply confidentiality controls and consent-aware sharing models for behavioral and mental health data experiences.
Standards & billing
We encode the reimbursement rules as product logic, so clean claims are the default and denials are the exception.
We map your payer mix to the RPM code rules (device-day counts, time tiers and modifier requirements) and design the billing data model.
Device-day counting and the per-month management timer, with interaction logging wired to clinician identity.
837P output with modifiers, ICD-10 linkage, and eligibility guards, validated against real denial patterns.
Connection to your billing system or clearinghouse, remittance (835) reconciliation, and denial dashboards.
RPM ROI worksheet
You work out RPM ROI by counting the patients who meet each code's rules in a month, multiplying each count by your payers' rate for that code, then subtracting device, staff and platform costs. Use your own numbers below; we supply no rates.
| Line | What you enter | How to work it out |
|---|---|---|
| 1. Setup | Patients newly enrolled this month | New patients x your rate for 99453 |
| 2. Device supply | Patients with 16 to 30 days of readings, and patients with 2 to 15 days | Each count x your rate for 99454 or 99445; a patient gets one or the other |
| 3. Management time | Patients with 10 to 19 minutes, patients with 20 minutes or more, and each further 20 minutes | Each count x your rate for 99470, 99457 or 99458; 99470 and 99457 are not billed together |
| 4. Monthly revenue | No new input | Lines 1 + 2 + 3 |
| 5. Device and data cost | Device, cellular data and replacement cost per monitored patient | Cost per patient x monitored patients |
| 6. Clinical staff cost | Minutes per patient per month and the staff hourly cost | Patients x minutes / 60 x hourly cost |
| 7. Platform and billing cost | Software, hosting, support and billing fees | Monthly total |
| 8. Monthly margin | No new input | Line 4 minus lines 5, 6 and 7 |
Rates differ by payer, locality and year, and the codes a patient qualifies for depend on that month's readings and documentation. Check the current CPT descriptors and your contracts; this worksheet is a planning aid, not a quote.
Short facts we design RPM billing software around, each linked to its primary source.
Medicare's remote physiologic monitoring codes include CPT 99453, 99454, 99457 and 99458, and the CY 2026 Physician Fee Schedule added 99445 and 99470 for shorter monitoring periods and shorter management time.
Source: Federal Register, November 5, 2025 (CY 2026 Physician Fee Schedule final rule, CMS-1832-F)CMS states in the CY 2026 Physician Fee Schedule final rule that the 2 to 15 day and 16 to 30 day device supply codes are not additive, and that 99470 (first 10 minutes) and 99457 (first 20 minutes) are not billed together: the practitioner picks the code that fits the month.
Source: Federal Register, November 5, 2025 (CY 2026 Physician Fee Schedule final rule, CMS-1832-F)HIPAA adopts ASC X12 standards for electronic transactions, including health care claims (837), payment and remittance advice (835), eligibility inquiries (270/271) and prior authorization requests (278).
Source: 45 CFR Part 162 (eCFR)The HIPAA Security Rule requires administrative, physical and technical safeguards for electronic protected health information.
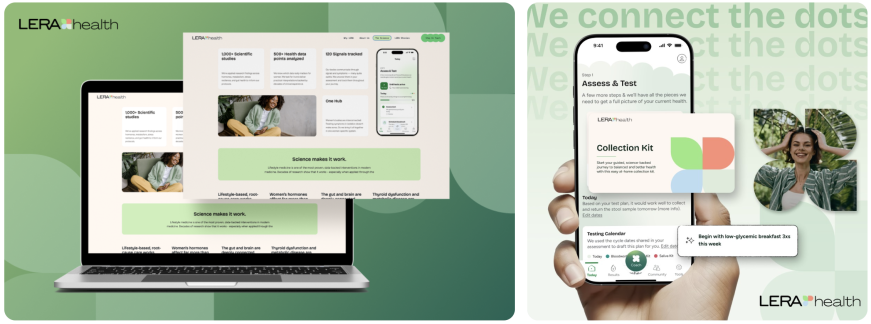
Source: 45 CFR Part 164 Subpart C (eCFR)Related proof of compliant delivery: for Lera Health we built precise, auditable data workflows connecting testing to care, the same rigor in tracking and documentation that defensible RPM billing depends on.
We treat reimbursement as software, so revenue doesn't leak at the thresholds.
Every reading and minute is logged against identity and time, so claims hold up when a payer looks.
Pre-claim eligibility and code-combination guards catch the errors payers deny for before submission.
We encode the device-day and time-tier rules precisely, not approximately: the difference between paid and clawed back.
837P output and 835 reconciliation into your existing billing system or clearinghouse.

RPM CPT billing tracked in the product and audit-ready
Tell us your codes and payer mix. We'll return a plan to enforce the RPM code rules in the product and generate clean, audit-ready 837P claims.
contact@agnotic.com
Partnerships
contact@agnotic.com


