

ACOs
Shared-savings tracking and quality reporting for accountable care organizations.



We build platforms that connect clinical outcomes to reimbursement: quality-measure tracking, risk-adjusted analytics, and contract dashboards that show, in near real time, where a value-based agreement stands against its targets.
Trusted by global innovators









Value-based care pays providers for outcomes and cost against agreed targets, while fee-for-service pays for each service delivered. Software for value-based care has to attribute patients, calculate quality measures, adjust for risk and project contract performance during the period. Agnotic Technologies builds that layer for ACOs, health plans and risk-bearing providers.
Generic BI dashboards can chart a number but can't trace it to the measure specification, attributed population and contract term behind it. We build VBC platforms where you can drill from a shared-savings projection to the gaps, patients and measures driving it.
What it is
A value-based care platform connects clinical outcomes to financial performance under risk-bearing contracts, computing quality measures, adjusting for population risk, attributing patients, and projecting earned reimbursement against contract targets.
Its job is to make performance visible early enough to act on. We build platforms where every outcomes-to-reimbursement number is traceable to its source, so care teams and finance can trust the same dashboard.
Quality measures, risk adjustment, and contract performance in dashboards that trace every number back to its source.

Each capability ties a value-based outcome to the data standard or measure spec that makes it defensible.
A model that maps clinical and claims data to contract terms (shared savings, capitation, bundled payments) so you can project earned revenue against benchmarks throughout the performance period, not just at reconciliation.
HEDIS, MIPS, and CMS Star measures computed from FHIR R4 clinical data and claims, with electronic clinical quality measure (eCQM) logic and gap-in-care detection that flags open measures while there's still time to close them.
HCC risk-score calculation and suspected-condition surfacing from clinical notes and claims, so risk-adjusted contracts reflect the true acuity of the attributed population.
Dashboards that show each value-based agreement against its targets (quality, cost, utilization) with drill-down from a top-line number to the patients and measures behind it and role-based views for executives and care teams.
Patient-to-provider and patient-to-program attribution logic, with panel management views so care teams know exactly who they're accountable for under each contract.
A FHIR R4 data layer aggregating EHR, claims, ADT, and lab feeds via HL7 v2 and bulk FHIR $export, with encryption and audit logging so the analytics rest on governed, traceable data.
Where it runs
Shared-savings tracking and quality reporting for accountable care organizations.
Contract performance and Star-rating management across networks.
Capitation and downside-risk monitoring for provider groups.
Cross-organization measure aggregation and attribution.
HCC risk-adjustment accuracy and Star measure closure.
Outcomes reporting for direct-to-employer arrangements.
Value-based performance is won during the period, not at reconciliation. We build for visibility early enough to act: targets are defined against your contracts in discovery.

Health Insurance Portability and Accountability Act
Protect PHI with privacy-first architecture, encrypted storage and transmission, strict access controls, and traceable audit logs.

General Data Protection Regulation
Implement lawful consent flows, data minimization, retention controls, and secure processing for sensitive health data.

Fast Healthcare Interoperability Resources
Enable standardized health data exchange across apps, care teams, and systems through standards-based FHIR APIs.

Health Level Seven International
Support enterprise-grade interoperability with HL7-based integrations for records, events, and clinical messaging workflows.

Health Information Trust Alliance
Align security programs to healthcare-specific control and risk management practices trusted by providers and ecosystem partners.

Health Information Technology for Economic and Clinical Health Act
Design with breach notification readiness, digital record safeguards, and operational controls that support regulated care programs.

FDA Software as a Medical Device
Plan software quality, traceability, and documentation pathways for products that may require SaMD review and submission.

Medical Device Regulation (European Union)
Prepare EU market-ready processes for risk classification, evidence tracking, and lifecycle governance under MDR expectations.

Substance Abuse and Mental Health Services Administration
Apply confidentiality controls and consent-aware sharing models for behavioral and mental health data experiences.
Standards we build against
Data aggregation, measure logic, and contract modeling run in parallel toward a defensible dashboard.
We map your value-based agreements, the measures that drive them, and your available data sources, then design attribution and measure logic before building.
We build the FHIR R4 data layer aggregating EHR, claims, and ancillary feeds, with the governance and lineage the analytics depend on.
Quality-measure calculation, risk adjustment, and the outcomes-to-reimbursement engine, validated against known reconciliation results.
Role-based contract dashboards with drill-down, gap-in-care worklists, and ongoing tuning as measure specs and contracts change year over year.
Fee-for-service vs value-based care
Most organizations run both payment models at once. The table shows what each one asks of the software, so you can see which parts of your stack already exist and which a value-based contract adds.
| Criteria | Fee-for-service | Value-based care |
|---|---|---|
| What is paid for | Each service billed on a claim | Outcomes, quality and total cost against contract targets |
| When payment settles | Claim by claim, after adjudication | Claims during the year, then shared savings or losses at reconciliation, or a fixed amount per member under capitation |
| Who carries financial risk | Mostly the payer | Shared with providers under one-sided or two-sided models |
| Patient attribution | Not needed to get paid | Decides which patients count toward each contract |
| Data the software needs | Charges, codes and claims | Claims plus clinical data, attribution lists and quality measure inputs |
| Core software functions | Charge capture, coding, claim submission and denial management | Attribution, quality measures, risk adjustment, gap-in-care worklists and contract modeling |
| Reporting rhythm | Per claim and month-end revenue reports | Running performance views, so teams act before the period closes |
| Where AI helps | Coding suggestions and denial prediction | Risk suspecting from notes, gap prediction and outreach priorities, with clinician review |
Contract terms differ by payer and program. We map your agreements in discovery before modeling any of them.
Short facts we design value-based care platforms around, each linked to its primary source.
The Medicare Shared Savings Program rules in 42 CFR Part 425 cover how Medicare fee-for-service beneficiaries are assigned to ACOs, quality performance standards and data sharing, and one-sided and two-sided payment models.
Source: 42 CFR 425.10 (eCFR)The HIPAA Security Rule requires administrative, physical and technical safeguards for electronic protected health information.
Source: 45 CFR Part 164 Subpart C (eCFR)A HIPAA covered entity may share protected health information with a business associate, such as a software vendor, only under a business associate agreement that commits the vendor to safeguard it.
Source: 45 CFR 164.502(e) and 164.504(e) (eCFR)The NIST AI Risk Management Framework is a voluntary framework that organizes AI risk work into four functions: Govern, Map, Measure and Manage.
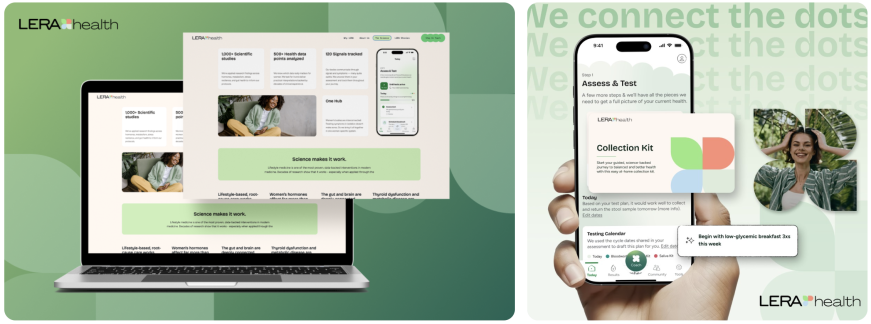
Source: NIST AI 100-1Related proof of compliant delivery: Lera Health isn't a VBC platform, but building its outcomes-driven data layer and auditable insights workflow shows how we turn clinical data into trustworthy, traceable analytics, the foundation any value-based platform stands on.
We combine measure-spec fluency, data-engineering depth, and compliance-first design so your VBC numbers hold up in reconciliation and audit.
Every outcome and dollar traces back to its measure spec, attributed population, and source data, built to survive payer reconciliation.
HEDIS, MIPS, eCQM, and HCC logic are our baseline, so measure calculation is engineered correctly rather than approximated.
Near-real-time gap and projection views so teams influence results while they still can, not after reconciliation.
We build for both sides of a value-based contract, aligning how outcomes are measured with how they get paid.

Analytics that hold up when the money is on the line
Tell us your value-based agreements and data sources. We'll return a VBC platform plan with measure scope, risk-adjustment approach, and a realistic timeline.
contact@agnotic.com
Partnerships
contact@agnotic.com


