

01
CMS file pipeline
Versioned loading and reconciliation of claims and assignment files.


A Medicare ACO runs on CMS files: assignment lists, claims and participant lists that change every quarter, plus notices beneficiaries must receive. Agnotic Technologies builds ACO software that loads and reconciles those files, tracks beneficiary notices and data sharing choices, checks SNF 3-day waiver eligibility and shows each participant its own performance.
Trusted by global innovators











ACO software is the operational system a Medicare accountable care organization uses to load CMS assignment and claims files, manage its participant list, track beneficiary notices and data sharing opt-outs, check SNF 3-day rule waiver eligibility and assemble quality reporting data. Agnotic Technologies builds it around the Shared Savings Program rules in 42 CFR Part 425.
The gaps we look for first, because each one is a program requirement, not a nice-to-have.
A new assignment list arrives, but the old one is still loaded in the care management tool, so outreach targets last quarter's beneficiaries.
A beneficiary declined data sharing, yet their claims still show in a participant's export.
Written notices were sent, but nobody tracked the follow-up communication or kept the record of how it was made.
A SNF admission without a 3-day stay is approved before anyone checks the beneficiary's assignment and the SNF's affiliate agreement.
A practice leaves the ACO, and the participant list and CMS notice are updated weeks later.
Missing substance use disorder claims are read by analytics as no care at all.
Three decisions we make with your ACO operations and compliance leads.
Each assignment list and claims delivery is loaded as a version, and every view says which version it uses.
Data sharing choices are enforced where data is read, so no report, export or app can show claims the beneficiary declined to share.
The SNF waiver check runs at the point of referral, using the current assignment list and the affiliate agreement on file.
Operations modules for Shared Savings Program ACOs. Quality measure engines and risk adjustment stay in your value-based care stack.
Claim and Claim Line Feed files and assignment reports loaded, checked and compared with the previous version.
TINs and NPIs with change requests, certification and termination tracking.
Signage, written notices and follow-up communications tracked per participant and beneficiary.
Opt-out flags from CMS files applied to every query, export and app.
Assignment, model and affiliate checks at referral, with the result stored.
Extracts from participant EHRs assembled for the quality data CMS asks for.
Each practice sees its own assigned beneficiaries, spending trends and open tasks.
Records of notices, checks and list changes kept for CMS on request.
The cycle we build for each CMS delivery, from download to participant views.
Claims and assignment files are downloaded and stored as a new version.
Record counts, beneficiaries added and removed, and file errors are checked against the last version.
Data sharing flags are applied before any data reaches reports or apps.
Each participant's beneficiaries and performance views are rebuilt from the new version.
Newly assigned beneficiaries get notice and follow-up tasks for their participant.
Care management and analytics tools receive the new version through an agreed interface.
Chosen to fit your participants' EHRs and your analytics stack. We build in your cloud account.
The table we fill with your ACO compliance lead. Each feature keeps the record that shows the rule was followed.
| Part 425 requirement | Software feature | Record that proves it |
|---|---|---|
| Beneficiary notification, 425.312(a) | Signage and notice tracker per participant site; written notice queue for assigned beneficiaries | Notice date, method and site per beneficiary |
| Follow-up communication, 425.312(a)(2)(v) | Follow-up task due within 180 days of the written notice | Follow-up date and how it was made available |
| Decline claims data sharing, 425.708 | Opt-out flag from CMS files suppresses identifiable claims in every view and export | Date the flag arrived and the suppression log |
| Substance use disorder claims, 425.708(c) | Analytics flag gaps instead of treating missing claims as no care | Rule version applied to each report |
| SNF 3-day rule waiver, 425.612 | Eligibility check at SNF referral: assignment, two-sided model and affiliate agreement | Check result, list version used and agreement on file |
| Participant list, 425.118 | TIN and NPI list with change requests and a 30-day termination notice task | List versions, certifications and change history |
Views we build with your ACO operations and medical leadership.
Beneficiaries added and removed, by participant.
Written notices sent and follow-ups due or late.
Waiver admissions by SNF affiliate, with check results.
Spending trends and open tasks for each participant.
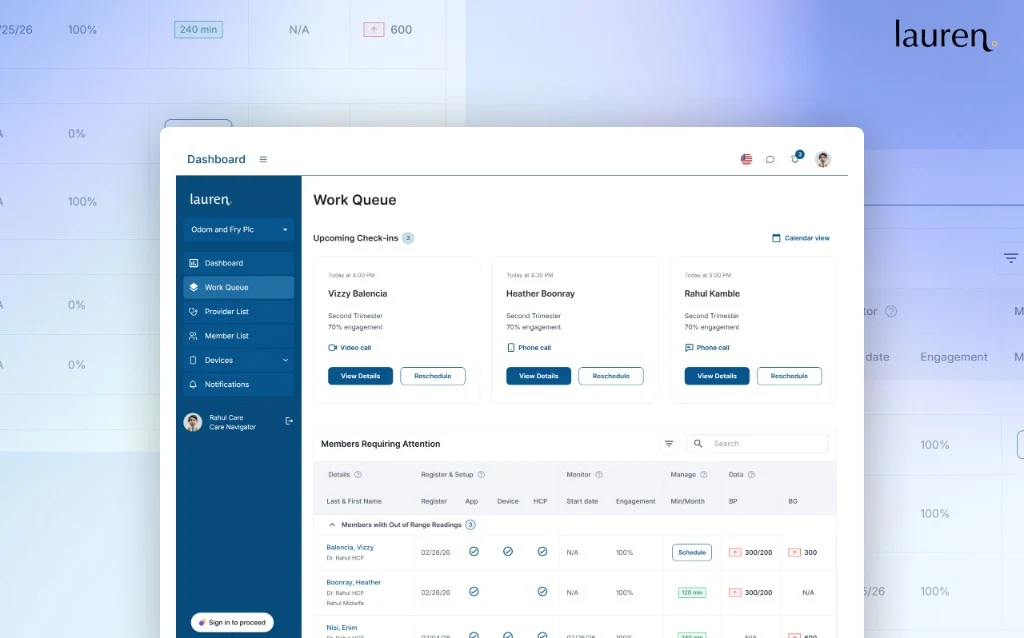
A HIPAA-ready maternal health platform enabling remote patient monitoring, care coordination, and personalized engagement from pre-pregnancy through postpartum.
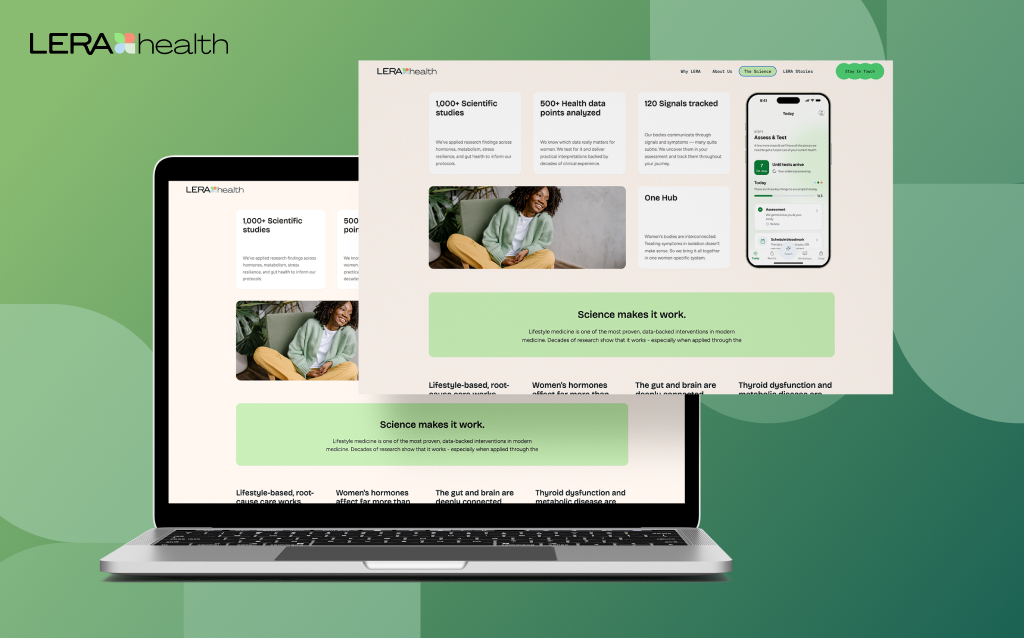
A women’s health product experience focused on guided care journeys, education, and compliance-aware workflows to support long-term engagement.
First releases we scope, each one tied to a program requirement.
Versioned loading and reconciliation of claims and assignment files.
Notices and follow-ups recorded per participant and beneficiary.
Referral-time eligibility check for SNF affiliates.
Practice-level views of assigned beneficiaries and tasks.
TIN and NPI changes, certifications and termination notices.
Operations tooling for an ACO entering its first agreement period.
The systems an ACO operations platform reads from or writes to, agreed during scoping.
We build secure, scalable products designed for privacy, interoperability, and regulatory readiness from day one across every sector we serve.

Protect PHI with privacy-first architecture, encrypted storage and transmission, and strict access controls.

Enabling standardized health data exchange through standards-based API mappings.

Supporting enterprise-grade interoperability for clinical messaging and record workflows.
We combine deep technical expertise with industry-specific knowledge to deliver solutions that aren't just functional, but transformational.
We implement rigorous security protocols and compliance standards (HIPAA, GDPR, SOC2) across all industrial solutions to protect sensitive data.
Our architectures are built to handle massive data loads and user bases, keeping performance steady whether you're serving ten or ten million.
Using our suite of internal tools and proven frameworks, we cut setup work so your first release reaches users sooner.
Beyond simple wrappers, we build deep-learning integrations and predictive analytics directly into the core of your industry-specific workflows.
The CMS file pipeline is the usual first requirement. We agree its boundaries and a delivery date with your operations lead.
We review your participants, current tools, CMS file handling and the first requirement.
Your compliance lead fills the rule-to-feature table with us.
One requirement end to end, with opt-out enforcement and audit records in place.
Practices are onboarded with their own access and views.
More requirements, integrations and file changes as CMS updates them.
Short facts we design the features and records around, each linked to its primary source.
A Shared Savings Program ACO must make sure beneficiaries are told that its participants take part in the program and that they can decline claims data sharing, through signs in participant facilities, written notices on request and a standardized written notice to assigned beneficiaries.
Source: 42 CFR 425.312(a) (eCFR)After the standardized written notice, the ACO or participant must follow up with the beneficiary verbally or in writing no later than 180 days later, and keep a record of each follow-up and how it was made available.
Source: 42 CFR 425.312(a)(2)(v) (eCFR)A beneficiary's request to decline claims data sharing stays in effect until the beneficiary contacts CMS to change it, and CMS does not share identifiable claims about substance use disorder diagnosis and treatment without the beneficiary's explicit written consent.
Source: 42 CFR 425.708 (eCFR)CMS waives the 3-day inpatient stay requirement before covered SNF care for eligible beneficiaries assigned to ACOs in a two-sided model, when the care is furnished by an eligible SNF that has a written affiliate agreement with the ACO.
Source: 42 CFR 425.612(a)(1) (eCFR)An ACO must maintain and submit an accurate list of each ACO participant with its Medicare-enrolled TIN and each ACO provider or supplier with its NPI, and notify CMS no later than 30 days after a participant agreement ends.
Source: 42 CFR 425.118 (eCFR)We don't just build products; we forge lasting partnerships. See how we've helped industry leaders transform their vision into technical reality.
“I can clearly see how Agnotic has a unique way of handling end-to-end development. They are always active on quick chat and provide support quickly.”

Aaron Phelan
Founder, Benchmark
“Agnotic combines deep technical expertise with strong domain knowledge. They understand the business context, anticipate challenges, and make collaboration smooth and effective.”

John Pasmore
Founder, Latimer
“Agnotic is the best technical team we evaluated. Their engineering excellence made our work dramatically easier and allowed us to stay focused on what matters most for maternal care outcomes. They took full ownership of the technical execution, and we are always happy to continue working together.”

Kim Smith
Founder, My Lauren
This page covers ACO operations under Part 425. These pages cover the analytics and care programs around it.
Attribution, quality measures and contract performance.
Risk stratification and care gaps across a population.
Care plans and outreach for high-risk patients.
Referrals and transitions between care settings.
The safeguards we build into every system that holds patient data.
Shared systems for management services organizations that run physician groups.
Explore other production-grade engineering platforms we deliver across healthcare.
The technical patterns behind this platform translate naturally into adjacent verticals.